AI Analytics for Healthcare Finance Teams: 2026 Guide
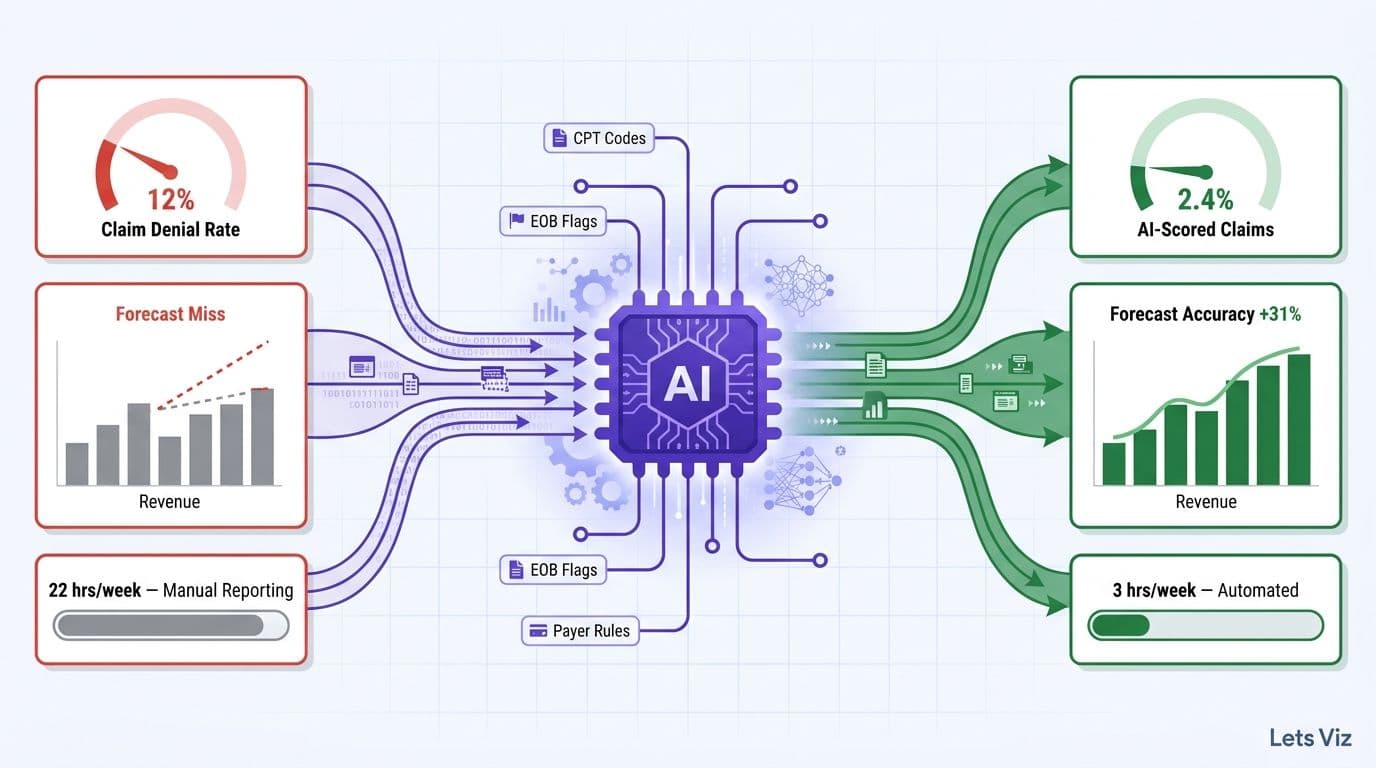
Hospital and health-system finance teams are deploying AI analytics to address three persistent financial problems: claim denial rates that erode net revenue by 5-15%, forecasting models that miss actuals by double-digit percentages, and manual reporting workflows that absorb 20 or more analyst hours each week. AI analytics for healthcare finance teams converts these reactive pain points into proactive, data-driven processes - improving cash flow predictability, reducing rework costs, and freeing finance staff for higher-value analysis.
Key Takeaways
AI claim scoring models flag denial-risk claims before submission, cutting first-pass denial rates by 20-35% in documented deployments
Predictive net revenue models incorporating payer contract data reduce forecast error from double-digit percentages to under 5%
Automated reporting pipelines free 15-25 analyst hours per week in mid-size health systems
Healthcare financial analytics investment continues to expand at a strong pace driven by value-based care adoption, regulatory change, and demand for real-time financial visibility across health system operations
A structured AI analytics strategy - beginning with two or three high-impact workflows - delivers faster ROI than deploying tools without a unified data foundation
What Is AI Analytics for Healthcare Finance Teams?
AI analytics for healthcare finance teams is the application of machine learning, predictive modeling, and automated reporting to the core financial workflows of hospitals, health systems, and medical groups. Primary use cases include claim denial prevention, net revenue forecasting, payer contract analysis, and operational cost variance monitoring.
Where traditional financial analytics explained what happened last quarter - which service lines missed budget, which payers denied at elevated rates - AI analytics projects what is likely to happen next week. A claim with a high denial probability is flagged before it leaves the billing queue. A revenue gap is visible three weeks before period close. A payer contract underperforming its modeled yield triggers an alert before the shortfall becomes material.
Finance teams that have worked primarily with business intelligence dashboards often find the shift to AI analytics disorienting at first. The output changes from a chart of last month's denial rate to an alert about which specific claims in today's batch are at risk. The workflow changes from reviewing what happened to acting on what is about to happen - which requires new escalation processes, not just a new dashboard.
The broader investment context supports this shift. AI consulting services and enterprise analytics platforms have expanded rapidly through 2025 and 2026, as regulated industries - healthcare prominently among them - have accelerated deployment ahead of earlier forecasts. Healthcare finance, with its complex payer environment and high cost of delayed cash, is one of the highest-return segments driving that growth.
The strategic framing matters: AI analytics is not a technology project. It is a financial performance program with specific, measurable targets - claim yield, forecast accuracy, cost of reporting - that should be defined before any tool is selected.
How Does AI Analytics Reduce Claim Denials in Healthcare?
AI analytics reduces claim denials by scoring each claim for denial probability before submission, giving revenue cycle teams time to correct coding, eligibility, or authorization errors before a payer rejects the claim. This upstream prevention model is meaningfully cheaper than working denials after the fact, which typically costs $25-$150 per rework as of 2026 and delays cash by 45-90 days.
A typical AI-assisted pre-submission claim workflow operates as follows:
The billing system exports each day's claim batch to an analytics layer
A machine learning model scores each claim on 40-80 features: payer ID, procedure code, diagnosis code pairing, prior authorization status, modifier logic, and patient eligibility
Claims scoring above a denial-risk threshold route to a coding specialist before submission
Weekly denial remittance data feeds back into the model, continuously improving accuracy over time
Payer-specific models go further. Training on 24 months of remittance history from a single commercial payer reliably surfaces systematic denial patterns - modifier pairs the payer never reimburses, diagnosis code combinations it flags as unbundled - that were never visible in aggregate reporting. For example, one regional health system trained a payer-specific model on 18 months of remittance data from its largest commercial payer and discovered that modifier -25 claims for evaluation and management services were being denied at a 64% rate when billed same-day as certain minor procedures - a pattern generating an estimated $320,000 in annual rework costs that had never surfaced in aggregate denial dashboards. Patterns like this often account for 30-40% of total denials but are invisible without payer-level model segmentation. As of mid-2026, the largest RCM platform vendors - including Epic's Denial Prevention module, Oracle Health's claim analytics suite, and Waystar - have begun embedding payer-specific denial scoring as a standard capability, making this segmentation accessible without custom model development for health systems already running these platforms.
Finance leaders tracking the right leading indicators will find the 5 Key Financial KPIs Every CFO Should Track framework directly applicable: first-pass claim acceptance rate, denial rate by payer, and net days in accounts receivable are the three metrics that quantify whether an AI claims model is generating measurable financial return.
How Do Finance Teams Use AI to Forecast Net Revenue?
AI-powered net revenue forecasting replaces static spreadsheet-based budget models - updated quarterly and directionally unreliable within 30 days of being built - with dynamic models that update daily using live payer mix, volume, and contract yield data. The result is a forecast that stays accurate as conditions shift rather than diverging progressively from actuals.
A well-structured AI revenue forecast for a health system incorporates four primary inputs:
Volume drivers - inpatient admissions, outpatient visits, and surgical cases broken out by service line and payer, updated daily from scheduling and billing systems
Payer contract modeling - expected yield per encounter by procedure and payer, drawn from historical remittance data rather than billed charges, which consistently overstate collectible revenue
Denial and adjustment reserves - dynamically sized based on current denial rate trends by payer and procedure type, not fixed historical percentages that lag real conditions by weeks when a payer changes its adjudication logic
Seasonality and trend adjustments - elective procedure demand shifts, post-holiday admission patterns, flu season volume spikes that alter payer mix and case acuity in ways static models cannot capture
Through 2025 and into 2026, health systems expanding risk-based contracting exposure have faced sharper pressure to close the gap between modeled and actual net revenue - a gap that static spreadsheet forecasting cannot reliably manage as payer mix and contract terms shift quarter to quarter. Net revenue forecasting is where value-based care pressure, payer analytics demands, and AI capability converge most directly for CFOs managing cash position against tightening margins.
For organizations already using Power BI for financial reporting, the analysis in AI + ARR waterfalls: what works, what still needs a human translates directly: the waterfall logic governing SaaS ARR bridges applies cleanly to net patient revenue period-over-period analysis and payer mix shift quantification.
What Does AI Analytics Do for Manual Reporting Burdens?
AI analytics eliminates the most time-intensive parts of the monthly financial reporting cycle - data extraction, payer reconciliation, variance commentary, and package distribution - compressing a five-to-seven-day process into one to two days. Mid-size health systems with automated reporting pipelines consistently report recovering 15-25 analyst hours per week, time that redeploys to contract modeling, cost analysis, and strategic scenario planning.
The table below maps the most common manual reporting tasks in healthcare finance against AI automation impact:
| Reporting Task | Manual Time Required | AI Automation Impact |
|---|---|---|
| Daily census and volume report | 2-3 hours/day | Automated overnight; ready at shift start |
| Weekly denial dashboard | 3-4 hours/week | Real-time payer-level view, zero assembly time |
| Monthly payer performance scorecard | 8-12 hours/month | Generated in under 30 minutes from live data |
| Period-close variance commentary | 6-10 hours/month | AI-drafted narratives; analyst review only |
| Board financial package assembly | 4-6 hours/month | Template-driven; auto-populated from approved data model |
Finance functions that benefit most from automation are high-frequency, rule-based data assembly tasks: daily census reports, weekly denial dashboards, and monthly payer performance scorecards. Functions that still require significant human time are those requiring judgment - explaining a variance driven by a strategic pricing decision, or advising the board on a reimbursement rate outlook that carries regulatory uncertainty. As of mid-2026, AI-generated variance commentary - once the automation claim that drew the most internal skepticism from senior finance staff - is now the most frequently cited time-saver by health system CFOs who have deployed Power BI Copilot or Microsoft Fabric AI narrative generation in production, marking a meaningful shift from experimental to standard workflow in a single fiscal year.
Before committing to a reporting platform, the AI Automation ROI Calculator: How to Measure What Matters provides a structured method for quantifying hours saved versus implementation investment - the right frame for presenting this case to a CFO or board finance committee.
What Is Clinical Data Management in Healthcare Analytics?
Clinical data management (CDM) in healthcare analytics is the process of collecting, validating, standardizing, and structuring clinical and operational data so it can feed reporting pipelines, AI models, and compliance workflows reliably. Hospital analytics directors increasingly need to understand CDM fundamentals not as a clinical informatics abstraction but as a practical prerequisite: the data discipline that determines whether a Power BI revenue cycle dashboard can be built on a single unified model or must be manually reconciled from disconnected billing exports every reporting cycle.
FHIR and HL7: The Data Standards Feeding Finance Pipelines
Two interoperability standards govern how clinical and financial data flows between systems in US health care:
*HL7 v2* - the messaging framework that has structured clinical data exchange since the 1980s - remains the dominant format for hospital billing and EHR system feeds. ADT (admit/discharge/transfer) messages, DFT (charge transaction) feeds, and ORU result messages are all transmitted as HL7 v2. A finance team building a revenue cycle pipeline in Power BI typically receives HL7 v2 streams from Epic Clarity, Oracle Health, or a clearinghouse aggregator. These feeds carry the raw encounter and charge data that populates A/R aging, denial rate, and net collection ratio visuals.
*FHIR R4* (Fast Healthcare Interoperability Resources) is the REST-based API standard that CMS mandated for payer-to-provider data sharing under the Interoperability and Patient Access Rule. Payers including CMS, United, and major Blues plans now publish member claims data and clinical summaries via FHIR APIs. For finance teams working on prior authorization analytics or payer contract performance monitoring, FHIR R4 data from payer APIs is becoming as important as the legacy HL7 v2 feeds from internal systems.
A CDM that maps both HL7 v2 transaction feeds and FHIR R4 payer resources into a unified dimensional model - encounter, patient, payer, service line - is what enables the revenue cycle dashboards described in the next section to filter correctly together rather than requiring manual joins. Without this mapping, analysts reconcile billing exports against clinical data by hand, which is the primary source of the 20-plus analyst hours per week that automated pipelines eliminate.
Compliance Obligations Under HIPAA and EU Clinical Trial Regulation
Two regulatory frameworks set the compliance boundaries that clinical data management in healthcare analytics must satisfy:
*HIPAA*: Any analytics pipeline handling protected health information (PHI) - which includes financial data tied to patient encounters - requires administrative, physical, and technical safeguards under the HIPAA Security Rule. For Power BI deployments specifically, this means row-level security limiting analyst access to appropriate patient populations, audit logging of data access events, data residency controls governing where encounter data is stored and processed, and Business Associate Agreements covering all analytics vendors, including Microsoft's cloud infrastructure for Power BI and Microsoft Fabric.
*EU Clinical Trial Regulation and ICH E6(R3) GCP*: Health systems running clinical trials or managing real-world evidence datasets under EU jurisdiction operate under EU Regulation No 536/2014 and the ICH E6(R3) Good Clinical Practice guidelines. These frameworks impose additional CDM requirements on top of HIPAA: full audit trails for any data modification, protocol deviation tracking, and source data verification to support regulatory submission. Finance teams at academic medical centers or integrated delivery networks participating in sponsored trials encounter these obligations when trial-linked encounter and cost data feeds into revenue or cost analysis - a boundary that finance and compliance functions need to coordinate on explicitly rather than treating as purely a clinical informatics responsibility.
How Structured CDM Connects to Power BI Reporting
When CDM is implemented correctly, the data model supporting HIPAA-compliant clinical operations and the data model feeding finance dashboards are the same model. Encounter-level data - validated, standardized, and consistently keyed across EHR, billing, and payer systems - flows into Power BI via Direct Query or scheduled refresh without manual transformation, making automated dashboard refresh reliable rather than aspirational. The practical starting points for a finance team inheriting or building a CDM-to-Power BI pipeline: confirm that patient encounter keys are consistent across EHR, billing, and payer remittance data (inconsistent encounter identifiers are the most common root cause of reconciliation gaps in healthcare finance dashboards); verify that FHIR R4 claim status resources from payer APIs are mapped to the same claim table as HL7 v2 DFT charges; and implement row-level security in Power BI aligned to the access controls in your CDM governance policy before sharing dashboards beyond the finance team.
How Do Healthcare Teams Structure Real-World Evidence Analytics from EHR Data?
Real-world evidence analytics for healthcare teams has moved from a primarily clinical research function to a core capability in hospital analytics departments - particularly those operating under value-based contracts, managing post-market surveillance obligations, or generating evidence for formulary and coverage decisions. The EHR data that finance teams already use for revenue cycle reporting is the same source data that feeds RWE study cohorts; the structural difference lies in study design, governance controls, and the regulatory standards the output must satisfy.
What FDA, EMA, and Health Canada Accept as Acceptable Evidence
Three major regulatory frameworks govern how RWE generated from EHR data can be used to support regulatory submissions or payer coverage decisions:
*FDA (United States):* Under the 21st Century Cures Act and the FDA's Real-World Evidence Program, the Agency accepts RWE from EHR data for post-approval drug effectiveness studies and, in select cases, label expansions. The FDA's September 2021 guidance "Real-World Data: Assessing Electronic Health Records and Medical Claims Data to Support Regulatory Decision-Making for Drug and Biological Products" specifies that EHR-sourced RWE must demonstrate data relevance (the EHR population reflects the target study population), data reliability (records are complete, accurate, and consistently collected), and study design validity (the observational design adequately controls for confounders). Randomized controlled trial evidence remains the primary standard for initial approval; RWE from EHR data is most accepted for post-market commitments, safety surveillance, and effectiveness studies in populations underrepresented in clinical trials.
*EMA (European Union):* The European Medicines Agency's DARWIN EU initiative - a federated network of validated real-world data sources launched in 2022 - represents the EMA's operational infrastructure for RWE-based regulatory decisions. Under EMA's methodological standards, EHR-based observational studies submitted in support of regulatory decisions must follow pre-specified protocols, use validated data sources with documented data quality frameworks, and apply appropriate epidemiological designs - active comparator new user designs are preferred over prevalent user analyses to reduce immortal time bias and confounding by indication. The EMA's joint guidance with the Heads of Medicines Agencies (HMA) specifically addresses distributed data network architectures that analyze EHR data without centralizing patient records across borders - a governance model that hospital analytics teams designing multi-site RWE studies in the EU should adopt to satisfy both EMA standards and GDPR Article 9 requirements for sensitive health data.
*Health Canada:* Health Canada's regulatory modernization framework, aligned with ICH E6(R3) Good Clinical Practice guidelines, accepts RWE from EHR data in support of post-market surveillance and conditional drug approvals. Health Canada's guidance emphasizes data provenance documentation - the complete chain of custody from point-of-care EHR capture through analytical dataset creation - and requires that missing data patterns be analyzed and addressed through pre-specified sensitivity analyses rather than excluded silently from results. The agency has signaled increasing receptivity to EHR-based RWE for real-world effectiveness evidence in therapeutic areas where trial enrollment is structurally difficult, such as rare diseases and pediatric indications.
Data Governance Requirements for EHR-Based RWE Studies
Structuring an EHR-sourced RWE study that satisfies any of these three regulatory frameworks requires governance controls that materially exceed the data quality practices most hospital analytics teams apply to revenue cycle reporting:
*Protocol pre-specification:* Regulatory-grade RWE requires a study protocol registered before data analysis begins. Exposure definition, outcome definition, covariate selection, and the statistical analysis plan must be locked prior to accessing the analytical dataset. This pre-specification requirement prevents the selective reporting bias that all three agencies specifically flag as a validity threat in observational EHR studies.
*Phenotype validation:* EHR computable phenotypes - the algorithms that identify study-eligible patients from diagnosis codes, medication orders, lab results, and procedure codes - must be validated against source records. Validation typically involves chart review of a random sample to confirm sensitivity and positive predictive value of each phenotype definition. Finance teams building condition-specific cost cohorts who skip phenotype validation risk misclassifying patients in ways that create material errors in cost-per-episode and readmission rate calculations, errors that compound when those outputs feed payer contract negotiations.
*Full audit trail for data transformations:* Every transformation applied to raw EHR data - cohort inclusion and exclusion logic, variable derivation, linkage to claims or lab data - must be documented in sufficient detail to be independently reproduced. This is a materially higher documentation standard than the ETL documentation typical in a finance reporting data warehouse, and it must be treated as a standing operational requirement rather than a one-time project deliverable.
*De-identification or IRB approval:* HIPAA Safe Harbor or Expert Determination de-identification is required for EHR data analyzed outside a covered entity's direct treatment operations. Studies that cannot be fully de-identified require Institutional Review Board approval and, in some cases, patient consent - particularly for studies linked to biobank, genomic, or longitudinal claims data.
Power BI Dashboard Architecture for RWE Study Management
Hospital analytics teams running RWE studies typically need a Power BI layer that serves two distinct audiences: the clinical research team managing study operations, and the finance or outcomes analytics team using RWE outputs for value-based contract performance or formulary decisions. A practical architecture separates these concerns across three report layers:
*Cohort tracking dashboard:* Monitors patient flow through study inclusion and exclusion criteria as EHR data refreshes. Key visuals include a CONSORT-style funnel showing enrolled versus excluded patients by criterion, exposure group balance on key covariates (age, comorbidity index, prior utilization), and a data completeness heatmap by variable and site. This layer connects to validated phenotype query outputs from the EHR, not to the operational billing tables used in revenue cycle dashboards - the two must remain structurally separate to preserve analytical dataset integrity required for regulatory submission.
*Outcomes tracking dashboard:* Tracks primary and secondary endpoints - readmission rates, length of stay, medication adherence, cost-per-episode - over the study observation window. Survival analysis visuals rendered via Power BI R visuals and time-to-event tables give the clinical team interim outcome data, while finance users see the same data reframed as cost and utilization metrics relevant to value-based contract performance.
*Data quality and audit dashboard:* Documents data completeness rates by EHR field and site, flags missing data patterns that require sensitivity analysis, and provides a full lineage view of ETL transformations applied to the analytical dataset. This layer is the one regulators examine during study audits, and the one internal audit functions need access to when RWE outputs inform payer contract negotiations or formulary submissions.
Row-level security in Power BI must restrict cohort-level patient data to IRB-approved study team members, while aggregate outcomes data can be shared more broadly with finance and strategy stakeholders. This access control architecture should mirror the data access controls documented in the study's data management plan - not be designed independently as a reporting-layer afterthought.
How Do You Build a Power BI Revenue Cycle Dashboard for Healthcare?
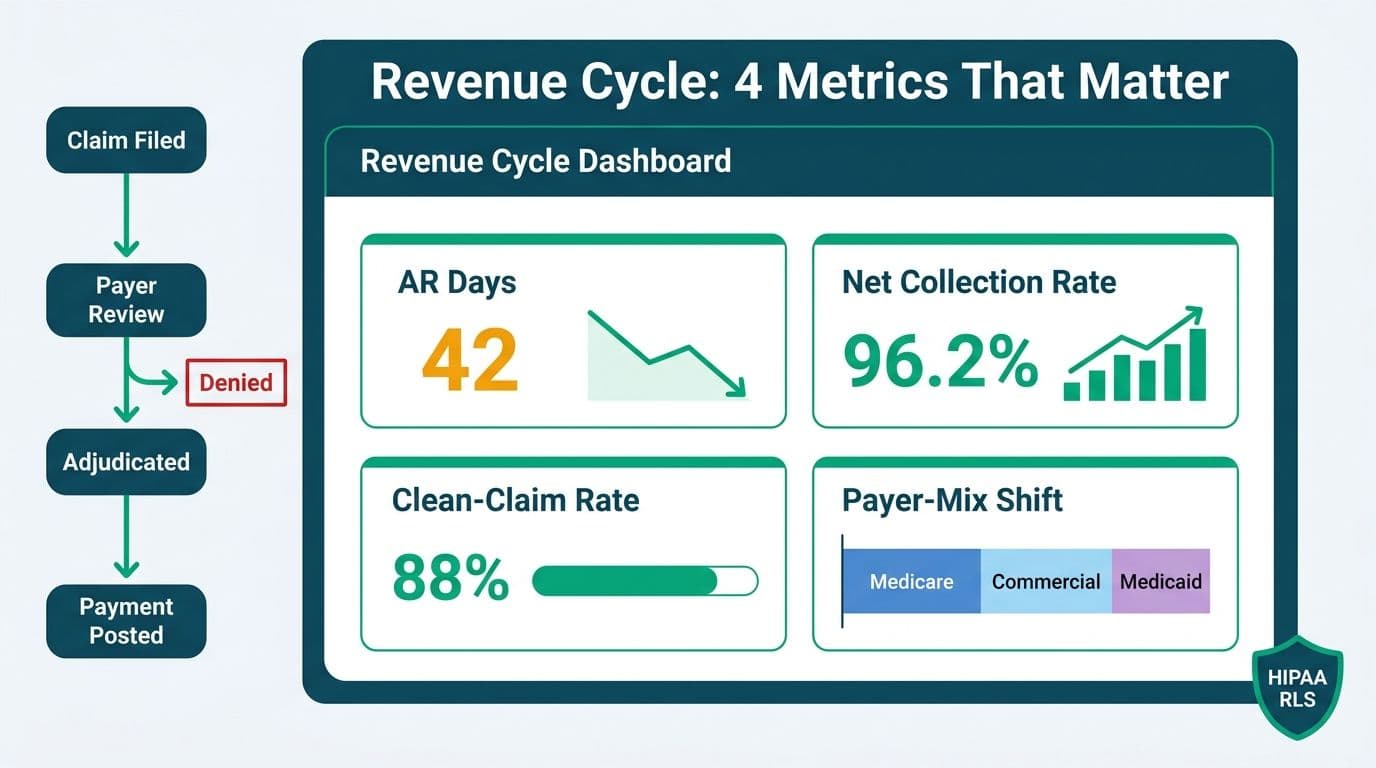
A Power BI revenue cycle dashboard for healthcare typically centers on three visuals that CFOs and revenue cycle directors review daily: A/R aging, denial rate by payer, and net collection ratio. The steps below assume a direct query or import connection to your billing system export - Epic Clarity, Oracle Health, or a flat file from your clearinghouse. Each section includes a brief Tableau equivalent for teams not yet on the Microsoft stack.
A/R Aging Dashboard
Power BI: Load your claims table and create an aging bucket column using a DAX SWITCH statement on `(TODAY() - ClaimDate)`, grouping into 0-30, 31-60, 61-90, 91-120, and 120+ day buckets. Build a stacked bar visual with Payer on the axis and a slicer for service line and facility. Add a KPI card for total A/R over 90 days as a percentage of total A/R - the industry benchmark is under 25%. Conditional formatting on the 120+ bucket in red creates an immediate visual threshold without a separate annotation layer.
Tableau equivalent: Use a calculated field with IF/ELSEIF logic for the same aging buckets. A stacked bar chart on the Payer dimension with a color encoding for bucket, combined with a line showing the 90+ trend over a rolling 13 months, achieves the same operational read.
Denial Rate by Payer
Power BI: Create a measure for denial rate using `DIVIDE([Denied Claims Count], [Total Claims Submitted])`. Plot a horizontal bar sorted descending so the highest-denying payer is always at the top. Add a drill-through page showing denial reason codes at the claim level. Apply conditional formatting - red above 10%, yellow between 5% and 10%, green below 5% - so threshold breaches are visible without a separate legend. Connecting this visual to the A/R aging model through a shared Payer key in your data model means both visuals filter together when a user selects a payer.
Tableau equivalent: A bar chart with a reference line at 10% and color rules via a calculated field achieves the same threshold signaling. Use a dashboard action filter to connect to a denial detail sheet for claim-level drill-through.
Net Collection Ratio
Power BI: Net collection ratio is `DIVIDE([Payments Received], [Expected Reimbursement])`, where expected reimbursement is contractual allowable - not billed charges, which overstate collectible revenue for most payer mixes. A line chart over rolling 12 months with a reference band between 95% and 98% immediately shows drift from the healthy range. Add a slicer for payer type (commercial, Medicare, Medicaid, self-pay) because blended ratios routinely mask payer-level underperformance that only surfaces when payer types are separated.
Tableau equivalent: A dual-axis chart with band annotations using reference lines at 95% and 98% accomplishes the same framing. A quick filter on Payer Type replaces the slicer.
The architectural decision that determines whether this healthcare revenue cycle dashboard in Power BI stays current automatically - or requires weekly manual refreshes - is connecting all three visuals through a single shared data model rather than maintaining separate workbooks per metric. Health systems that build the shared model upfront find the incremental cost of adding a fourth or fifth visual (net days in A/R, cost-to-collect) close to zero; those that build visuals independently spend disproportionate time reconciling numbers that should agree by construction.
When Should a Health System Invest in AI Analytics?
A health system should begin building an AI analytics program when three conditions are present: financial data connected across billing, EHR, and payer systems; a finance team that uses dashboards regularly; and at least one manual process consuming more than 10 analyst hours per week. Waiting for perfect data is a common and costly mistake - AI models improve faster on live imperfect data than on delayed clean data.
The right entry point depends on where financial pain is largest:
Claim denial rate above 8% - Start with AI-assisted pre-submission claim scoring. This is the fastest ROI path, typically producing measurable improvement within 60-90 days and a clear cash impact within the same quarter.
Net revenue forecast error above 10% - Start with payer contract modeling and dynamic volume forecasting. This is a 3-6 month project, but it produces compounding returns as the model improves with each billing cycle.
Finance team spending more than 20 hours per week on report assembly - Start with automated reporting pipelines. Power BI with AI-assisted narrative generation is the most accessible entry point for health systems already in the Microsoft ecosystem.
For mid-market health systems building an AI analytics strategy for the first time, a phased approach - denial prevention first, forecasting second, reporting automation third - is more reliable than attempting all three simultaneously before a data foundation is in place. Each phase produces data that improves the next phase's models. Health systems that try the full build-out in a single program typically run into data governance delays that stall the entire initiative.
Before selecting tools or vendors, the CFO's 6-question AI risk checklist for Power BI outlines the governance questions that should be answered upfront - model auditability, data lineage, user access controls, and regulatory compliance implications for AI-generated financial outputs.
AI-Powered Power BI Consulting for Finance Teams: What to Expect
AI-powered Power BI consulting for finance teams translates the capabilities described above into the reporting environment health system finance teams already use - replacing shadow spreadsheets, disconnected billing exports, and manually assembled board packages with automated dashboards that update without analyst intervention.
A well-scoped implementation typically runs in three phases:
Phase 1: Data foundation (4-6 weeks) - Connect billing system, EHR, and payer remittance data into a unified financial data model. Standardize core metrics: net revenue per encounter, denial rate by payer, cost per case by service line, and days in accounts receivable.
Phase 2: AI analytics layer (6-8 weeks) - Build claim denial scoring and net revenue forecast models. Integrate outputs into Power BI dashboards with alert thresholds, trend indicators, and automated variance commentary generation.
Phase 3: Reporting automation (4-6 weeks) - Automate monthly financial package distribution, daily operational dashboards, and board reporting templates. Train the finance team on interpreting AI-generated analysis alongside their own domain judgment.
Investment in healthcare financial analytics continues to expand at a strong pace, driven by regulatory change, value-based care adoption, and demand for real-time financial visibility. Health systems that build this infrastructure now are establishing the analytical foundation that payer contracting, cost management, and strategic planning will depend on over the next decade - not just solving a current reporting bottleneck.
For finance teams evaluating AI analytics consulting engagements, the AI Consulting Services for Financial Advisors: 2026 Guide outlines how to assess a provider's data architecture, modeling depth, and implementation track record before committing to an engagement.
---
If your health system finance team is ready to reduce claim denials, sharpen net revenue forecasting, and recover analyst hours currently lost to manual reporting, Managed Power BI services from Lets Viz deliver end-to-end implementation - from data architecture through AI-assisted dashboards - built specifically for healthcare finance workflows.
---
About Lets Viz: Lets Viz is a data analytics and AI consulting firm with over a decade of experience helping finance teams in healthcare, financial services, and mid-market organizations convert raw operational data into actionable business intelligence. Our consultants have delivered AI analytics programs across hospital revenue cycle, payer contract modeling, and CFO reporting workflows, using Power BI, enterprise EHR integrations, and value-based care performance platforms. We serve clients across the US, UK, and India, bringing both technical implementation depth and financial domain expertise to every engagement.